

Insertion
Impella RP Flex™ IJ Insertion into Cadaver
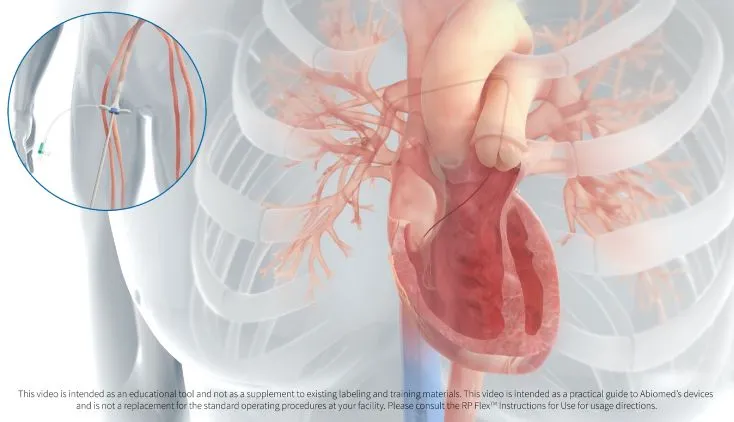
This video demonstrates how to insert the Impella RP FlexTM via the internal jugular (IJ) vein of a patient using a cadaver model. The steps are summarized below. Refer to the Instructions for Use (IFU) for complete instructions.
First, the video describes the steps for obtaining internal jugular access and preparing to insert the Impella RP Flex.
Confirm purge fluid is exiting the Impella Catheter
Obtain access to the internal jugular using ultrasound guided micro-puncture technique
Under fluoroscopic guidance, insert a 5 – 8 Fr indroducer over the 0.035 inch guidewire (provided) to pre-dilate the vessel.
Place a hemostatic stitch prior to removal of the 5 – 8 Fr introducer but do not secure down
Remove the 5 – 8 Fr introducer over the 0.035 guidewire. Under fluoroscopic guidance, insert the 8 Fr, 12 Fr, 16 Fr, and 20 Fr dilator sequentially, as needed. Remove the 20 Fr dilator and insert the 23 Fr introducer with pre-loaded dilator. Under fluoroscopic guidance, while inserting the 23 Fr introducer, hold the shaft of the introducer to advance it into the vein.
Administer systemic anticoagulation. When ACT is at least 250 seconds, remove the 23 Fr dilator and the 0.035 inch guidewire.
Attach a flush syringe to the 23 Fr introducer sidearm and aspirate and flush the 23 Fr introducer
Under fluoroscopic guidance, insert a 0.035” compatible flow-directed catheter into the 23 Fr indroducer and advance it into the left or right PA.
Form a curve on the 0.027” placement guidewire and insert it into the flow-directed catheter.
Under fluoroscopic guidance, advance the placement guidewire deep into the PA branch until wire prolapses.
Utilize a fixed wire technique to remove the balloon-tipped catheter over the 0.027” guidewire, leaving the wire in the PA branch.
The video then describes the steps for inserting the Impella RP Flex and initiating support.
Confirm hemostatic stitch is in place.
Attach a Flush Syringe and flush the repositioning sheath prior to advancing the sheath.
Place two dead-end caps on the repositioning sheath stopcock to prevent further usage. The sideport should not be used to give medication or draw blood because the blood could potentially clot. Pressure bags should not be connected to the sideport of the repositioning sheath.
Remove the 23 Fr peel-away introducer completely from the vein over the catheter shaft utilizing a pin and pull technique to ensure pump positioning is maintained. Once the sheath is out of the body, apply manual pressure at the venotomy.
Grasp the two wings of the 23 Fr Introducer and bend back until the valve assembly splits. To do this, first stretch then snap the flexible valve mechanism that temporarily holds the two wings together. Continue to peel the two wings until the introducer is completely separated from the catheter shaft. NOTE: Do NOT peel the 23 Fr peel-away introducer over the tip of the repositioning sheath.
Under fluoroscopic guidance, Slide the repositioning sheath over the catheter shaft while securing the catheter to maintain pump positioning and advance it into the vein to the distal tip of the suture pad.
Secure the previously placed hemostatic stitch.
Make sure there is no bleeding at the transition from the repositioning sheath to the vein.
Secure the repositioning sheath by suturing it to the skin using the suture ring on the sheath.
Verify placement with fluoroscopy, the position of the outlet area of the cannula should be at the level of the PA bifurcation with the pigtail deviating towards the left or right PA approximately 4 cm past the pulmonary valve annulus
Connect the Tuohy-Borst on the anticontamination sleeve to the repositioning sheath hub and turn the Tuohy-Borst clockwise to lock the T-lock in place. Secure the catheter shaft in place by holding both halves of the Tuohy-Borst and rotating the proximal side to tighten.
Carefully extend the anticontamination sleeve to maximum length and secure the end closest to the blue Impella plug by tightening the Tuohy-Borst at the proximal end of the anticontamination sleeve.
Dress the access site per hospital protocol.
Before leaving the procedural suite, when the pump access site is above the diaphragm, secure the catheter externally with a fixation point on either side of the blue plug. The catheter may be secured near the Tuohy-Borst of the anticontamination sleeve and on either side of the blue plug.
Related Content
IMP-7046